By Chancy Namadzunda, contributor:
In the twinkling of an eye, her life’s most precious commodity was gone.
It was her darkest hour as she imagined her life slipping away.
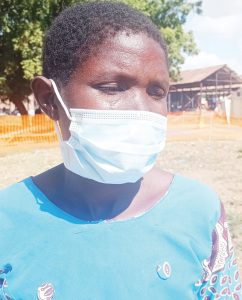
“I can’t forget that morning. We went to bed with optimism for the following day, but God had other plans. Our lives changed that night,” Christina Kenason, 40, says.
The married mother of five children, who is a farmer and businesswoman, comes from Chimtedza Village, Traditional Authority Mlolo in Nsanje District.
- Advertisement -
The district was one of the hardest hit by Cyclone Freddy, which claimed over 1,200 lives and displaced at least 650,000 others countrywide.
All her family members survived. But as Kenason tried to salvage of what was left of her possessions, she realised she had lost her drugs for tuberculosis (TB) together with her health passport.
“My heart skipped a beat. That was a stab in my flesh that morning,” Kenason, who was a few months into TB treatment, says.
The nearest health centres, where she could hope to replace the drugs, were Mbenje and Makhanga, but both facilities were submerged in water.
- Advertisement -
- Advertisement -
According to the World Health Organisation, skipping TB treatment not only leads to the TB bacteria developing resistance to medication but also makes a patient more infectious to others.
The floods, triggered by what was described by the World Meteorological Organisation as the strongest storm to hit the southern hemisphere, not only submerged health centres, but also destroyed roads and bridges, making it difficult for people to find refugee elsewhere.
Luckily, Kenason was among people rescued by Malawi Defence Force soldiers almost a week after the heavy rains had diminished.
The survivors were taken to Bangula evacuation camp.
The camp, which was the largest in the district, housed over 37,668 people who were displaced by the floods.
“All that time, I was not taking drugs and spent days without food. I was just praying to live another day. I was hopeless,” Kenason says.
After a few days at the camp, the gods smiled at her when medical personnel, who were conducting integrated mobile clinics, made a visit.
“That was when I saw the light,” Kenason says.
Searching for the affected
Of Nsanje’s 15 health facilities, 14 are TB active sites, according to District Nursing and Midwifery Officer Chancy Banda Fundani.
“Generally, Nsanje is prone to floods which occur yearly, disturbing the provision of health services. However, Cyclone Freddy was something else.
“We had four health facilities which got submerged in water. Roads were cut off and bridges destroyed.
Provision of health services in some areas was disrupted because their health centres were inaccessible,” Fundani says.
She adds that TB patients had their health passports washed away.
“It mostly affected those who were in the intensive period, who have just started TB treatment and needed follow ups,” the nurse says.
From January to March, during which period the area was impacted by the cyclone, medical personnel failed to screen for TB in some health centres.
“For example, we had no case at Makhanga Health Centre, but we registered only five cases at Mbenje, yet we normally register not less than eight cases in every quarter,” Fundani says.
At the start of the floods, she says, Nsanje District had 20 patients on treatment.
After the floods, health authorities organised teams to conduct integrated mobile outreach services in camps.
Luckily, they managed to track all the patients and brought them back to care.
According to Adzafunika Alfazema, Bangula TB Focal Person, the camp has 13 TB cases five of whom were diagnosed at the centre.
Risk of default among patients
According to Alfazema, some of the patients went to the camp with their health conditions deteriorating.
“These people had spent days without taking food or drugs,” he says.
Even though Kenason was back on treatment, she found the going tough because she would, on some days, take the TB drugs on an empty stomach.
“On some lucky days, I eat once, thanks to my ageing mother who receives food parcels from the camp,” she says.
In the camp, the elderly and children are prioritised in food provision.
Just like Kenason, Patrick Gauti, who comes from Magonyo Village in the same TA, also laments taking TB drugs on an empty stomach.
“It is difficult for us to take the drugs without food as these are strong drugs. We are just hoping for normal rations soon,” he says.
Alfazema says the issue of food is also a big concern to the leadership of the camp.
“Some patients are defaulting TB treatment because there is no food at the camp as they fear taking drugs would have negative effects on them,” he says.
According to the World Food Program (WFP), TB patients and people living with HIV need more calories and nutrients in their diets in order to strengthen their immune system, but they often have poorer appetites and are less able to absorb the nutrients in their food.
WFP encourages the integration of a comprehensive food and nutrition component in the HIV and TB treatment and support package which it says is critical in ensuring better health outcomes for people living with these conditions.
Alfazema says they are currently reaching out to well-wishers and other stakeholders so that they should put these patients on the priority list or they should have special allocations.